
Medical Tourism Blog
Cleft Lip Surgery in Korea: Types, Timing, Travel Planning and Aftercare

Table of contents
- Cleft Lip Surgery at a Glance
- What Is Cleft Lip Surgery?
- Who Is a Good Candidate for Cleft Lip Surgery?
- What Are the Different Types of Cleft Lip Surgery?
- Why Visit Korea for Cleft Lip Surgery?
- Key Information for International Patients
- Which Are the Best Clinics in Korea for Cleft Lip Surgery?
- Cleft Lip Surgery From Start to Finish
- Alternatives to Cleft Lip Surgery
- How Can I Prepare for Cleft Lip Surgery?
- Aftercare Advice
Considering treatment in Korea? Everything you need to know e.g. — how to avoid scams, visas, interpreters, recovery tips — in our Medical Tourism Master Guide. Plan with confidence in minutes, not weeks!
Last updated: September 2026
Cleft Lip Surgery at a Glance
- What it repairs — Primary cleft-lip repair, or cheiloplasty, uses general anesthesia to reconnect the upper-lip skin, lining, vermilion, and orbicularis oris muscle; limited nasal correction may be performed at the same operation.
- Typical timing — Repair is commonly performed at 3–6 months of age once an infant is feeding, gaining weight, hydrated, and medically suitable for anesthesia.
- Recovery and early result — Selected healthy infants may go home the same day, while others need overnight or longer monitoring; swelling and bruising peak in the first several days, wound review is usually around 1 week, and scar maturation takes about 6–12 months.
- Long-term cleft care — Lip repair does not close a cleft palate or address all future needs; depending on anatomy, care can later include palate surgery, hearing and speech services, orthodontics, alveolar bone grafting, nasal treatment, or revision.
- Travel to Korea — International families should plan about 10–14 days in Korea for assessment, surgery, observation, and the postoperative wound check; the surgeon and pediatric anesthesia team—not a fixed flight rule—must clear travel home.
- Korea-specific consideration — Korea has documented cleft-care activity, but public data do not compare hospital- or surgeon-level cleft outcomes, complications, revision rates, interpreter quality, or international follow-up; confirm the individual cleft team and home-country handover plan.
- When to postpone — Fever, respiratory infection, vomiting, diarrhea, dehydration, poor weight gain, anemia, or unoptimized airway, heart, or other medical conditions commonly require delaying surgery until the child is medically ready.
What Is Cleft Lip Surgery?
Cleft lip surgery is an operation that closes a congenital gap in the upper lip and restores its continuity. It aims to improve feeding, lip function, facial balance, and the foundation for ongoing cleft care as a child grows. It is a surgical procedure performed under general anesthesia.
Who Is a Good Candidate for Cleft Lip Surgery?
- Medically ready infants — Primary cleft-lip repair is commonly performed at about 3–6 months when the infant is feeding, gaining weight, hydrated, and suitable for general anesthesia.
- Unilateral or bilateral cleft lip — Children with a complete or incomplete cleft on one side or both sides can be assessed for primary repair.
- Families pursuing coordinated cleft care — Good candidates have access to a multidisciplinary plan covering feeding, hearing, speech, dental/orthodontic, palate, alveolar, nasal, and later revision needs.
- Selected wide clefts — Infants with a wide cleft can be considered for presurgical infant orthopedics, such as nasoalveolar molding (NAM), before repair when the team considers it useful.
Active respiratory infection, fever, vomiting, diarrhea, dehydration, poor weight gain, anemia, or an uncorrected medical problem commonly requires postponement and optimization first. Prematurity-related concerns, congenital heart disease, airway obstruction or sleep-disordered breathing, and suspected syndromes require individualized pediatric, anesthesia, and cleft-team assessment; they can also require overnight admission rather than routine discharge. Primary repair is not cosmetic lip surgery and is not interchangeable with palate repair, later lip revision, or definitive cleft rhinoplasty. Families traveling from overseas should defer travel-based surgery when they cannot stay for postoperative monitoring and an early wound check or cannot arrange reliable cleft and pediatric follow-up at home.
What Are the Different Types of Cleft Lip Surgery?
Cleft-lip repair is tailored to the cleft pattern, the upper-lip muscle separation, nasal distortion, and whether the gum ridge or palate is also involved.
- Unilateral cleft lip — A cleft on one side of the upper lip. It can be complete, extending toward the nostril, or incomplete.
- Bilateral cleft lip — Clefts on both sides require reconstruction of the central lip segment and both nasal bases and are often more complex.
- Cleft lip only, lip with alveolus, or lip with palate — Alveolar involvement affects the gum ridge and later dental planning. A palate cleft needs separate repair; lip surgery does not close it.
- Primary cheiloplasty — The first congenital repair, usually undertaken in infancy, reconnects the skin, vermilion, mucosal lining, and orbicularis oris muscle.
- Primary repair with nasal correction — The surgeon can reposition the nasal base or cartilage during lip repair. This limited primary correction differs from a later definitive cleft rhinoplasty.
- Secondary cheiloplasty — A later cheiloplasty can address scar contracture, vermilion notching, muscle discontinuity, or persistent asymmetry.
- Presurgical NAM — Nasoalveolar molding can help selected wide clefts align alveolar segments and improve nasal and lip form before surgery. It is an adjunct, not a substitute for repair, and requires frequent in-person adjustments.
Why Visit Korea for Cleft Lip Surgery?
South Korea has an established domestic population requiring cleft care and pediatric reconstructive surgery. National data support the presence of cleft-related surgical activity, but they do not prove that every hospital offers equivalent long-term results or international continuity of care. Verify the specific pediatric cleft team, anesthesia service, language support, and handover plan rather than relying on country-level claims.
- Documented domestic cleft-care need — A nationwide cohort identified 11,284 children with cleft lip with or without palate among 5,747,830 live births in Korea between 2006 and 2018, an annual prevalence of 1.96 per 1,000 live births; a separate analysis found most cleft lip and palate surgery occurred within the first five years of life. These figures describe national burden and utilization, not individual surgeon outcomes.
- Potential multidisciplinary access — Cleft care can require pediatric plastic or craniofacial surgery, pediatric anesthesia, feeding support, ENT/audiology, speech-language therapy, dentistry/orthodontics, and genetics. Confirm which services are directly available and which will transfer to the child’s home country.
- Technique should match anatomy — Millard rotation-advancement, Fisher anatomical subunit, and Tennison-Randall designs are established options for unilateral repair. Comparative evidence does not establish a universally superior design, so the useful question is why a team recommends its design for the child’s anatomy.
- Limits of Korean outcome data — Korean claims research reports utilization, institution type, stays, visits, and costs, but does not provide comparable public hospital- or surgeon-level aesthetic, functional, complication, revision, interpreter, or international follow-up outcomes. This is an important evidence limitation for overseas families.
Key Information for International Patients
- Plan 10–14 days locally — This cautious planning window allows in-person assessment, testing, surgery and observation, then wound review at roughly postoperative day 7. It is not a universal evidence-based minimum.
- Do not set flights before clearance — There is no cleft-lip-specific safe-to-fly interval. The CDC’s 10–14-day advice applies to major surgery, particularly chest or abdominal surgery, and should not be applied mechanically to infant cheiloplasty. The operating surgeon and pediatric anesthesia team must clear departure after assessing feeding, hydration, airway status, wound integrity, and follow-up arrangements. CDC medical-tourism guidance also emphasizes continuity-of-care planning.
- Expect an early review — Swelling and bruising are usually most noticeable in the first several days. An incision check is commonly arranged about one week after surgery, so do not book sightseeing, intercity travel, or departure around that appointment.
- Prepare for possible overnight care — Carefully selected healthy infants can sometimes go home the same day after repair, while children with airway, feeding, age, or medical concerns need overnight or longer monitoring. Evidence supports outpatient repair only for appropriately selected patients.
- Arrange home-country handover before travel — Secure a pediatrician and, where possible, a local cleft team willing to receive records and monitor healing, feeding, scar care, and later developmental needs.
- Obtain complete English records — Before departure, collect operative and anesthesia reports, discharge instructions, medication and feeding plans, information on sutures, adhesive, or nasal retainers, emergency contacts, and the written handover plan.
Travel note: A parent or legal guardian needs to remain with the child for consent, hospital care, continuous observation after discharge, and the early postoperative review.
Which Are the Best Clinics in Korea for Cleft Lip Surgery?
Listed below are some of the best clinics in Korea for cleft lip surgery.
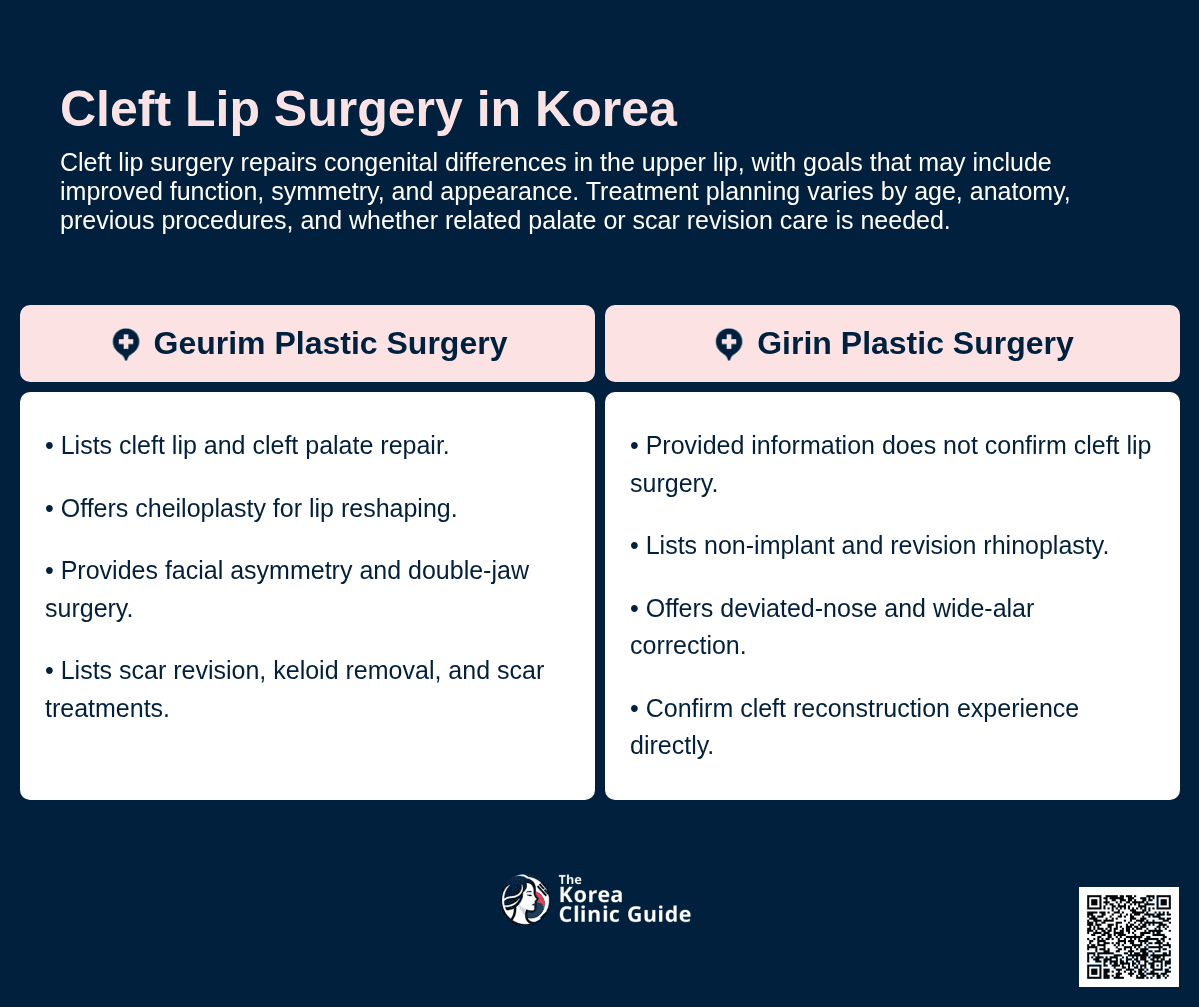
1. Geurim Plastic Surgery
You may consider Geurim Plastic Surgery for cleft lip surgery because its listed specialized procedures explicitly include cleft lip and cleft palate repair, alongside reconstructive options that may be relevant to functional restoration and appearance. The clinic also lists cheiloplasty and scar-revision treatments, which may be pertinent when discussing your individual lip shape, function, and scar concerns with the surgical team.
- URL: Geurim Plastic Surgery Website
- Location: Seoul
- Cleft and reconstructive procedures:
- Lists cleft lip surgery and cleft palate surgery for repair of congenital lip and palate anomalies.
- Lists cheiloplasty, a procedure for reshaping the lips with aesthetic and functional considerations.
- Lists double-jaw surgery and facial-asymmetry correction among its reconstructive and facial surgical offerings.
- Scar-related options:
- Lists scar revision surgery, burn-scar treatment, keloid removal, atrophic-scar treatment, and acne-scar treatment.
- Lists hair transplantation on scars as an additional scar-masking service.
2. Girin Plastic Surgery
Girin Plastic Surgery’s provided information does not confirm that it performs cleft lip surgery or cleft-related reconstruction. Its listed surgical scope does include rhinoplasty, alar narrowing, revision rhinoplasty, and other facial procedures, but you should confirm directly whether it offers cleft lip repair and whether your care would be managed by a surgeon with relevant reconstructive experience.
- URL: Girin Plastic Surgery Website
- Location: Seocho-gu, Seoul
- Related facial and nasal surgery scope:
- Lists nasal procedures including non-implant rhinoplasty, deviated-nose correction, wide-alar surgery, and revision rhinoplasty.
- Lists facial contouring procedures, including genioplasty and zygoma reduction.
- Lists revision eye and [revision breast surgery](/blog/revision-breast-surgery-korea), indicating that revision procedures are part of its stated service range.
Cleft Lip Surgery From Start to Finish
- Remote consultation and records review — Send clear facial and intraoral photographs, feeding and growth history, birth and pediatric records, medication and allergy lists, prior operative reports, and any cardiac, airway, genetic, or prematurity information. Request written confirmation of English communication options, anticipated appointments, and the postoperative stay required.
- In-person cleft-team assessment — The team confirms whether the child has isolated cleft lip, alveolar involvement, cleft palate, nasal deformity, or associated anomalies. Assessment includes feeding, hydration, weight gain, breathing, ear or hearing concerns, and the family’s capacity for follow-up.
- Pediatric anesthesia review and targeted testing — Disclose snoring, apnea, wheezing, asthma, recent cough or cold symptoms, previous anesthesia, heart conditions, medicines, and supplements. Testing and specialty clearance depend on the child’s history and are not identical for every infant.
- Preoperative readiness check — Report new fever, respiratory symptoms, vomiting, diarrhea, or contagious-illness exposure. The team can postpone surgery when illness makes anesthesia or airway management unsafe.
- General anesthesia and primary repair — Under general anesthesia, the surgeon aligns the mucosa, vermilion, skin, and orbicularis oris muscle to restore lip continuity and upper-lip landmarks. Planned primary nasal-base or cartilage repositioning can be performed during the same anesthetic.
- Post-anesthesia observation and feeding — Staff monitor breathing, oxygenation, bleeding, pain, nausea, and feeding. Discharge requires stable breathing, adequate feeding, controlled pain, and a safe observation plan; some children stay overnight or longer.
- Local recovery and wound review — Keep the child near the hospital and attend the planned review at about one week. The team assesses the incision, feeding, hydration, any nasal device, and readiness for onward travel.
- Return-home handover and remote follow-up — Share Korean operative and discharge records with the home pediatric and cleft teams. Maintain remote contact with the operating team as arranged, while local clinicians oversee urgent concerns and long-term cleft care.
Alternatives to Cleft Lip Surgery
No nonsurgical option closes a clinically significant cleft lip or reconnects separated orbicularis oris muscle. The meaningful choices are temporary deferral when anesthesia is unsafe, presurgical adjuncts, or related staged procedures for a different anatomical problem.
Delayed Primary Repair
- When it is used — Deferral is appropriate for acute illness, dehydration, inadequate feeding or weight gain, anemia, unstable airway concerns, cardiac issues, or other conditions that require optimization.
- Tradeoff — It avoids operating before medical readiness but does not correct the cleft during the delay. The cleft team sets revised timing based on health and growth.
Nasoalveolar Molding
- What it does — NAM or other presurgical infant orthopedics can guide alveolar segments and nasal/lip shape in selected wide clefts before surgery.
- Tradeoff — It does not replace primary repair and requires frequent adjustments, which is often impractical for a short international trip.
Cleft Palate Surgery
- What it addresses — Cleft palate surgery closes a palate cleft when one is present and is planned separately from lip repair.
- Tradeoff — It addresses palatal anatomy and later speech-related function, not the separated upper lip. Children with cleft lip and palate often need both procedures at different stages.
Secondary Lip or Nasal Reconstruction
- What it addresses — Secondary cheiloplasty or cleft rhinoplasty can address later scar contracture, lip asymmetry, vermilion notching, or nasal asymmetry.
- Tradeoff — These procedures refine residual concerns after growth and healing; they do not replace primary infant repair.
How Can I Prepare for Cleft Lip Surgery?
- Send records early — Provide pediatric, birth, feeding, growth, cardiac, airway, genetic, vaccination, medication, allergy, and previous-anesthesia records before travel. Include clear photographs requested by the cleft team.
- Report illness immediately — Contact the hospital before travel and again before surgery for fever, cough, wheezing, significant runny nose, vomiting, diarrhea, poor feeding, or contagious-illness exposure. Do not travel assuming a sick child can proceed as scheduled.
- Follow fasting instructions exactly — Use the hospital’s written fasting schedule. Breast milk, formula, solid food, and clear liquids have different cutoff times; formula and milk are not clear liquids.
- Review every medicine and supplement — Give the anesthesia team a complete list, including prescribed drugs, vitamins, herbal products, and traditional remedies. Do not stop essential medication independently; obtain specific instructions for anything affecting bleeding, sedation, or fasting.
- Protect feeding and hydration — Bring familiar bottles, nipples, breast-pumping supplies if relevant, formula or feeding equipment approved for travel, and a written baseline of normal feeding and wet diapers.
- Book practical accommodation — Stay near the hospital through the early wound review. Reserve accommodation with reliable refrigeration or preparation facilities if needed for feeds, and avoid a demanding tourist itinerary.
- Travel with a guardian and flexible plans — A parent or legal guardian must be available for consent and continuous care. Keep return flights flexible because illness, feeding concerns, admission, or wound findings can delay departure.
- Arrange follow-up before departure — Identify the home pediatrician and cleft team, confirm how they will receive records, and ensure international calling and secure document access are available.
Travel note: Seek travel-health advice 4–6 weeks before departure and discuss the infant’s immunizations, flight exposure, destination-specific risks, and medical-travel plan.
Confirm the treating hospital’s clinic-specific fasting, medication, admission, feeding, and travel requirements; its individualized instructions take precedence over general guidance.
Aftercare Advice
Protect the repair, maintain feeding and hydration, and treat breathing or feeding changes as urgent concerns rather than routine postoperative discomfort.
- Monitor breathing and alertness — Seek emergency care for breathing difficulty, blue or gray color, unusual inability to wake, or repeated vomiting, then notify the operating team.
- Track feeding and wet diapers — Give prescribed pain medicine exactly as directed and monitor milk intake and urine output. Contact the team urgently for refusal to feed, substantially reduced wet diapers, or signs of dehydration.
- Follow the assigned feeding method — Available evidence supports immediate breast- or bottle-feeding after isolated cleft-lip repair when the operating team permits it, and does not support routine arm restraints. The evidence has limits and protocols vary, especially with nasal devices, combined palate procedures, or feeding difficulties.
- Protect the incision — Prevent rubbing, trauma, and unapproved contact with the lip. Do not apply ointment, cleanser, tape, silicone, scar massage, or other products unless the surgeon has given exact instructions.
- Watch for wound problems — Contact the clinic promptly for persistent bleeding, wound separation, rapidly increasing swelling, pus, foul drainage, fever according to the team’s threshold, or pain not controlled by prescribed medicine.
- Attend early and long-term follow-up — Keep the wound review at about one week. Redness and firmness can persist for weeks; scar maturation commonly takes 6–12 months. Once the incision has fully healed, the team can advise on silicone, massage, and sun protection.
- Plan staged cleft care — Lip repair is one stage of care. Palate treatment, hearing and speech monitoring, orthodontics, alveolar bone grafting, nasal treatment, or later revision depend on the child’s anatomy and development.
Follow the treating doctor’s written instructions over general advice, and contact the clinic promptly whenever feeding, breathing, the incision, or the child’s behavior appears wrong.
Frequently Asked Questions
Related Blogs

Discovering the True Cost of Keloid Ear Surgery: Korea vs. Global Alternatives
Discover the cost of keloid ear surgery in Korea, where advanced medical techniques combine with affordability to offer effective treatment options. Learn about factors influencing prices and why many choose Korea for their cosmetic and reconstructive surgery needs.
Updated: Sep 27, 2026

Comparing Costs: Why Korea Is a Top Destination for Foreign Body Removal vs Global Alternatives
Discover the costs and procedures involved in Foreign Body Removal in Korea, a popular destination for affordable and high-quality medical care. Learn about the factors influencing prices and how Korea's healthcare system ensures safe and efficient treatments for overseas patients.
Updated: Sep 26, 2026

Discover the Global Spectrum of Scar Removal Surgery Costs and Why Korea Leads the Way
Discover how much scar removal surgery costs in Korea, a popular destination for affordable cosmetic procedures. Explore factors influencing the pricing and what to expect during your medical journey in this comprehensive guide.
Updated: Sep 25, 2026

Otoplasty in Korea: Methods, Recovery, Risks and Travel Planning
Otoplasty reshapes or repositions outer-ear cartilage for prominent ears, asymmetry, and selected congenital or revision concerns, usually as a 1–3 hour outpatient procedure using sutures, cartilage modification, or both. International patients planning treatment in Korea should allow 10–14 days for assessment, early wound review and possible suture removal, follow activity and dressing restrictio
Updated: Sep 21, 2026

