
Medical Tourism Blog
Cleft Palate Surgery in Korea: Methods, Recovery, Travel Planning, and Long-Term Care

Table of contents
- Cleft Palate Surgery at a Glance
- What Is Cleft Palate Surgery?
- Who Is a Good Candidate for Cleft Palate Surgery?
- How Is Cleft Palate Surgery Performed?
- Why Visit Korea for Cleft Palate Surgery?
- Key Information for International Patients
- Which Are the Best Clinics in Korea for Cleft Palate Surgery?
- Cleft Palate Surgery From Start to Finish
- Alternatives to Cleft Palate Surgery
- How Can I Prepare for Cleft Palate Surgery?
- Aftercare Advice
Considering treatment in Korea? Everything you need to know e.g. — how to avoid scams, visas, interpreters, recovery tips — in our Medical Tourism Master Guide. Plan with confidence in minutes, not weeks!
Last updated: September 2026
Cleft Palate Surgery at a Glance
- Purpose and timing — Primary palatoplasty is reconstructive surgery that closes the opening between the mouth and nose and rebuilds soft-palate muscle function; it is commonly performed at 9–14 months and ideally completed by 18 months when the child is medically ready.
- How repair is done — Under general anesthesia, the surgeon closes the nasal and oral layers of the palate and reconstructs the levator-muscle sling using an anatomy-specific approach such as intravelar veloplasty, Furlow Z-plasty, or a buccal flap.
- Hospital recovery — An uncomplicated primary repair commonly requires 1–3 nights in hospital, with discharge based on stable breathing, pain control, and adequate fluid intake rather than a fixed length of stay.
- Early healing — Swelling, nasal congestion, sleep disruption, and reduced intake are often greatest in the first few days, and the repair needs protection from unsuitable foods and objects in the mouth for several weeks under the operating team’s feeding protocol.
- Long-term care — Palate closure does not guarantee typical speech or hearing; ongoing cleft-team follow-up may include speech therapy, ENT and audiology care, dental and orthodontic treatment, and sometimes further surgery.
- Key risk — Palatal fistula, or a reopening between the mouth and nose, is a notable complication; one systematic review reported an overall incidence of 8.6%, although rates vary substantially by cleft type and reporting methods.
- Korea travel planning — International families should plan to stay in South Korea for at least 2–3 weeks after discharge for early review, use changeable flights, obtain individualized fitness-to-fly clearance, and arrange a written handoff to a qualified cleft team at home; Korean outcome research does not establish superior results over other established multidisciplinary cleft systems.
What Is Cleft Palate Surgery?
Cleft palate surgery is reconstructive surgery that closes an opening in the roof of the mouth and restores soft-palate function. It aims to support feeding, swallowing, and speech development while separating the mouth from the nose. It is a surgical procedure performed under general anesthesia.
Who Is a Good Candidate for Cleft Palate Surgery?
- Infants with a cleft involving the palate — Primary palatoplasty closes the separation between the mouth and nose and rebuilds soft-palate muscle function. It is commonly performed between 9 and 14 months when the child is medically ready, with repair ideally completed by 18 months.The ACPA parameters of care
- Children with feeding or functional concerns — Nasal escape of milk or food, swallowing difficulty, and an unrepaired opening between the oral and nasal cavities require assessment by a cleft team.
- Patients needing a secondary repair — Older children, adolescents, and adults with a palatal fistula, persistent nasal regurgitation, or structural velopharyngeal insufficiency after prior repair can need revision assessment.
- Families able to commit to long-term care — Surgery is one stage of cleft treatment. Speech-language assessment, hearing and ENT care, dental and orthodontic surveillance, and later procedures remain possible throughout childhood.Team-based, longitudinal cleft care
Cleft palate surgery is reconstructive rather than cosmetic surgery. Untreated airway obstruction, severe obstructive sleep apnea, significant micrognathia or Pierre Robin sequence-related airway difficulty can require postponement or specialist pediatric anesthesia planning. Acute respiratory infection, fever, dehydration, poor growth, uncontrolled pulmonary disease, relevant anemia or bleeding disorders, and uncoordinated anticoagulant or antiplatelet treatment can also make elective surgery unsafe. An asymptomatic submucous cleft without important nasal regurgitation, hypernasality, or velopharyngeal dysfunction can be monitored instead of repaired immediately; the cleft surgeon must assess anatomy, airway safety, nutrition, development, and family capacity for postoperative care.
How Is Cleft Palate Surgery Performed?
Palatoplasty methods are selected according to cleft width and location, available tissue, levator-muscle anatomy, prior repair or scarring, airway considerations, and speech goals. All established approaches use general anesthesia, close the nasal and oral surfaces in layers, and aim to restore the levator-muscle sling.ACPA guidance on functional palate repair
- Straight-line repair with intravelar veloplasty — The surgeon closes the palate along the cleft and repositions abnormally oriented soft-palate muscles to create a functional sling. It is an established option when anatomy supports this design.
- Furlow double-opposing Z-plasty — Opposing Z-shaped tissue flaps lengthen and reconstruct the soft palate while repositioning muscle. It is useful in selected primary and secondary repairs, but suitability depends on tissue availability and cleft anatomy.
- Buccal-flap-assisted palatoplasty — Tissue from the inner cheek supplements palatal tissue, particularly when cleft width or tissue deficiency makes tension-free closure difficult.
- Evidence limits — A 2023 systematic review reported pooled subsequent speech-correcting surgery rates of 19% after straight-line palatoplasty, 6% after Z-palatoplasty, and 7% with buccal flaps. These figures do not prove that one method is best: cleft phenotype, syndromic diagnoses, Robin sequence, timing, surgeon experience, speech-therapy access, and outcome definitions differed substantially across studies.Review of technique outcomes and reporting limitations
Why Visit Korea for Cleft Palate Surgery?
South Korea has pediatric hospitals and surgical departments that provide cleft-palate treatment within broader craniofacial care. For an overseas family, the important advantage is access to a coordinated pediatric cleft pathway, not a promise of superior surgical results. Confirm that the proposed hospital can provide pediatric anesthesia, ENT/audiology, feeding support, speech services, emergency assessment, interpretation, and a written handoff to the home team.
- Documented Korean clinical experience — Published work from Seoul Asan Medical Center includes clinical cleft-palate outcome data, while Korean national claims studies describe treatment timing, service use, and later treatment patterns.Korean cleft-palate clinical research
- Multidisciplinary model — International families should seek a program structured around the disciplines recommended for cleft care: surgery, pediatrics, anesthesia, ENT and audiology, feeding support, speech-language pathology, dentistry and orthodontics, and genetics or psychosocial care when indicated.ACPA team-care framework
- Important evidence limitation — Available Korean research is principally single-center or claims-based. No Korea-wide, risk-adjusted comparative registry was identified showing that primary palatoplasty in Korea produces better speech, fistula, or patient-reported outcomes than other established multidisciplinary cleft systems.Korean national treatment-pattern research
- Continuity before convenience — Require written confirmation that the Korean team accepts the case, will review the child before travel, and can communicate operative details and follow-up needs to a qualified cleft team near home.
Key Information for International Patients
- Minimum stay — Plan to remain in South Korea for at least 2–3 weeks after discharge for an uncomplicated primary repair. This is a conservative planning interval for early wound, feeding, hydration, pain, and airway review—not a universal evidence-based rule for flying.
- Hospital admission — Uncomplicated primary palatoplasty commonly requires 1–3 nights of inpatient observation. Discharge depends on stable breathing, adequate pain control, and sufficient oral fluid intake, not on a fixed number of nights.Postoperative priorities in cleft care
- Flights home — Do not book a non-changeable return flight. Recovered general anesthesia alone does not automatically prevent air travel, but postoperative fitness to fly depends on airway status, bleeding, hydration, feeding, complications, and access to emergency care at the destination.Aerospace Medical Association guidance
- Higher-risk children — Pierre Robin sequence, micrognathia, obstructive sleep apnea, syndromic diagnoses, respiratory illness, poor intake, concurrent ENT surgery, or any airway event require individualized clearance from the cleft surgeon and pediatric anesthesia team.
- Itinerary impact — Keep the first weeks focused on hospital review, quiet accommodation, feeding routines, and rest. Avoid changing cities, long day trips, or activities that make urgent reassessment difficult.
- Remote follow-up — Arrange a named cleft or craniofacial team near home before departure. Obtain the operative report, anesthetic summary, discharge instructions, medication list, and direct contact pathway for the Korean surgical team.
Travel note: No cleft-palate-specific, evidence-based air-travel interval was identified. The operating team’s written clearance takes precedence over general travel guidance.
Which Are the Best Clinics in Korea for Cleft Palate Surgery?
Listed below are some of the best clinics in Korea for cleft palate surgery.
1. Girin Plastic Surgery
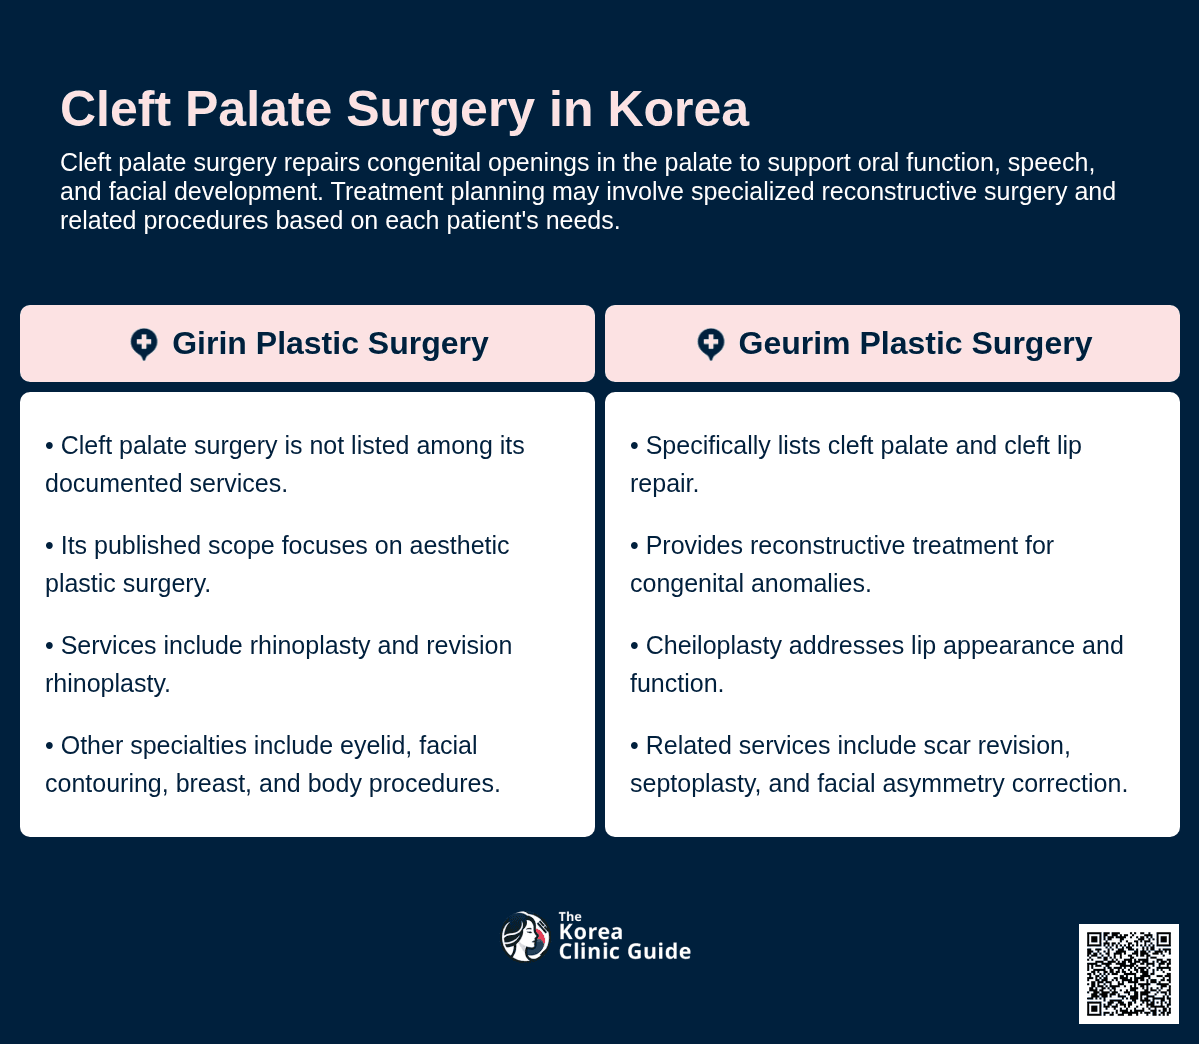
Girin Plastic Surgery’s provided information does not list cleft palate surgery, so you should not assume this procedure is available there. Its documented surgical services focus on aesthetic plastic surgery, including rhinoplasty, facial contouring, eyelid procedures, breast surgery, and body contouring.
- URL: Girin Plastic Surgery Website
- Location: Seocho-gu, Seoul
- Documented surgical scope:
- Nose procedures include non-implant rhinoplasty, correction of deviated, flat, humped, long, short, and wide-alar noses, and revision rhinoplasty.
- Eye procedures include ptosis correction, upper and lower blepharoplasty, double-eyelid surgery, canthoplasty, and revision eye surgery.
- Facial procedures include zygoma reduction, V-line surgery, genioplasty, facelift, and mini facelift.
2. Geurim Plastic Surgery
You may consider Geurim Plastic Surgery for cleft palate surgery because its listed specialized procedures explicitly include cleft lip and cleft palate repair for congenital lip and palate anomalies. The clinic also lists reconstructive and functional facial procedures that may be relevant when a broader treatment plan is needed.
- URL: Geurim Plastic Surgery Website
- Location: Seoul
- Cleft and reconstructive procedures:
- Cleft palate surgery and cleft lip surgery are listed as specialized procedures for repair of congenital anomalies.
- Cheiloplasty is listed for lip reshaping with attention to appearance and function.
- Scar revision, burn-scar treatment, keloid removal, and foreign-body removal are also listed.
- Related facial services:
- Double jaw surgery is listed to correct and align the upper and lower jaws for function and aesthetics.
- Facial asymmetry correction and nasolabial-angle adjustment are listed among facial procedures.
- Septoplasty is listed to straighten a deviated septum and improve breathing.
Cleft Palate Surgery From Start to Finish
- Initial records review — Send cleft photographs, feeding and growth history, prior operative reports, medication and allergy lists, anesthesia history, respiratory and sleep history, and available ENT, hearing, speech, dental, orthodontic, or genetic records. Ask whether a virtual consultation and professional English interpretation are available.
- Cleft-team assessment and travel plan — The team confirms whether surgery is appropriate, identifies airway or nutritional concerns, discusses the planned repair, and coordinates the expected admission and early review schedule. Secure a home-team handoff before travel.
- Preoperative evaluation in Korea — The pediatric surgical and anesthesia teams assess cleft anatomy, current feeding and growth, airway and sleep symptoms, medical diagnoses, and suitability for general anesthesia. Testing is ordered when the child’s history or examination requires it.
- Anesthesia and repair — The child receives general anesthesia. The surgeon creates layered closure of the nasal and oral palate and reconstructs the levator-muscle sling using a straight-line/intravelar veloplasty, Furlow Z-plasty, buccal flap, or another anatomy-appropriate approach.
- Inpatient observation — Staff monitor breathing, oxygenation, bleeding, pain, fluid intake, and feeding. Swelling, nasal congestion, reduced intake, and disrupted sleep are often most pronounced during the first few days.
- Discharge teaching — Before discharge, caregivers receive the center’s exact instructions for medicines, diet progression, bottles, cups, syringes, straws, pacifiers, utensils, mouth protection, and warning signs. Evidence on the best post-palatoplasty feeding method is limited and conflicting, so follow the operating center’s protocol rather than generic online rules.Review of postoperative feeding evidence
- Early Korean follow-up — Attend the scheduled wound and feeding review before leaving the country. The surgeon checks healing, hydration, pain control, airway status, and whether travel clearance is appropriate.
- Return-home and remote follow-up — Share the operative and discharge records with the home cleft team. Continue scheduled speech, hearing, ENT, dental, orthodontic, and surgical surveillance; contact the Korean team remotely as arranged.
Alternatives to Cleft Palate Surgery
There is no nonsurgical treatment that closes a clinically significant primary cleft palate. Alternatives apply only when a submucous cleft is asymptomatic or when a patient has residual fistula or velopharyngeal dysfunction after earlier surgery. Speech therapy can treat learned speech patterns but cannot close a structural gap.ACPA guidance on cleft-related speech and structural management
Observation
- Best suited to — An asymptomatic submucous cleft without clinically important hypernasality, nasal regurgitation, or velopharyngeal dysfunction.
- Tradeoff — Avoids immediate surgery but requires cleft-team surveillance because speech, feeding, or resonance concerns can become clearer with development.
Palatal Obturator or Speech Prosthesis
- Purpose — A removable appliance can temporarily or selectively separate the oral and nasal cavities or improve speech resonance when surgery is unsuitable, deferred, or declined.
- Tradeoff — It does not reconstruct muscle anatomy, requires dental/prosthodontic expertise and ongoing adjustments, and is not a substitute for primary repair in most infants.
Revision Palatoplasty or Fistula Repair
- Purpose — Secondary surgery closes a symptomatic fistula or revises a prior repair when anatomy causes nasal escape, poor closure, or other functional concerns.
- Tradeoff — Scar tissue, tissue shortage, cleft anatomy, and airway factors make revision planning more individualized than primary repair.
Velopharyngeal Insufficiency Surgery
- Purpose — A procedure directed at the velopharyngeal mechanism can be considered after formal speech and instrumental assessment confirms a structural cause of persistent hypernasality.
- Tradeoff — Speech therapy remains important for articulation errors, while structural surgery carries airway implications and needs specialized evaluation.
How Can I Prepare for Cleft Palate Surgery?
- Send complete records early — Provide cleft, feeding, growth, respiratory, sleep, anesthesia, allergy, medication, hearing, ENT, speech, dental, orthodontic, and genetic information. Send prior operative reports and imaging when applicable.
- Report current illness immediately — Tell the team about fever, cough, runny nose, wheeze, vomiting, diarrhea, reduced intake, or reduced urination. An acute respiratory illness or dehydration can require postponing elective anesthesia.
- Review every medicine and supplement — List prescription drugs, over-the-counter medicines, vitamins, herbal products, anticoagulants, and antiplatelet drugs. Do not independently stop prescribed medication; the surgeon and anesthesiologist must provide medication-specific instructions.
- Follow fasting instructions exactly — The pediatric anesthesia team will specify when to stop solids, formula, breast milk, and clear liquids. Do not use an online fasting schedule in place of the hospital’s instructions.
- Support nutrition and hydration — Discuss poor growth, feeding fatigue, aspiration concerns, and formula or feeding-device needs before travel. Nutritional status affects readiness for surgery and recovery.
- Plan continuous caregiving — Bring a parent or legal guardian able to stay throughout admission and provide uninterrupted care after discharge. Book quiet, nearby accommodation with reliable refrigeration, laundry, and easy access to the hospital.
- Keep travel flexible — Arrange changeable flights and avoid commitments after the planned departure date. Bring translated medical records, insurance details, essential feeding supplies approved by the operating team, and enough routine medication for the stay.
Travel note: Confirm in writing who will provide urgent assessment after discharge, how to reach the team outside office hours, and which clinician will clear the child for the flight home.
Confirm all clinic-specific preoperative requirements with the treating surgeon and pediatric anesthesia team; their instructions take precedence over this general guidance.
Aftercare Advice
Protecting the repair, maintaining hydration, and recognizing airway or bleeding problems early are the priorities after cleft palate surgery.
- Feeding and mouth protection — Follow the operating team’s exact liquids, purees, and soft-food progression and its rules for bottles, cups, syringes, straws, pacifiers, utensils, fingers, and toys in the mouth. The repair is vulnerable during the first several weeks.
- Pain and fluids — Give prescribed pain medicine exactly as directed and track fluid intake and urination. Contact the team promptly when pain prevents drinking, intake drops substantially, or urination is clearly reduced.
- Activity and sleep — Keep activity calm during early healing and use any elbow restraints only as instructed. Expect temporary swelling, nasal congestion, disrupted sleep, and reduced intake, particularly in the first few days.
- Wound and follow-up — Attend all scheduled postoperative reviews. Do not pull at stitches or attempt to inspect or clean the palate beyond the center’s instructions; report a visible opening, foul drainage, pus, or persistent new nasal escape of food or liquid.
- Urgent warning signs — Seek urgent medical assessment for breathing difficulty, persistent noisy breathing, blue or gray color, substantial or persistent bleeding from the mouth or nose, repeated vomiting of blood, fever with clinical deterioration, or inability to maintain fluids.
- Long-term function — Healing of the palate does not confirm normal speech or hearing. Continue cleft-team surveillance for speech-language development, velopharyngeal function, middle-ear disease and hearing, dental development, orthodontics, facial growth, fistulae, and the potential need for later treatment. Reported fistula incidence was 8.6% across 9,294 patients in one systematic review, with substantial variation by cleft type and reporting method.Systematic review of fistula and secondary-surgery outcomes
Follow the treating doctor’s written instructions over general advice, and contact the clinic immediately when healing, breathing, feeding, or behavior appears wrong.
Frequently Asked Questions
Related Blogs

Otoplasty in Korea: Methods, Recovery, Risks and Travel Planning
Otoplasty reshapes or repositions outer-ear cartilage for prominent ears, asymmetry, and selected congenital or revision concerns, usually as a 1–3 hour outpatient procedure using sutures, cartilage modification, or both. International patients planning treatment in Korea should allow 10–14 days for assessment, early wound review and possible suture removal, follow activity and dressing restrictio
Updated: Sep 21, 2026

Varicose Vein Treatment in Korea: Methods, Recovery, Travel Planning, and Safety
Varicose vein treatment begins with standing duplex ultrasound mapping and may use laser or radiofrequency ablation, vein glue, mechanochemical ablation, foam sclerotherapy, phlebectomy, or surgery based on anatomy and risk factors. The article covers candidacy, recovery, compression and walking guidance, follow-up, warning symptoms, and travel planning including flight restrictions after treatmen
Updated: Sep 19, 2026

Hyperhidrosis Laser in Korea: Methods, Recovery, Results, and Travel Planning
Laser treatment for primary axillary hyperhidrosis uses subdermal fiber ablation through tiny incisions or surface laser sessions to reduce underarm sweating, with repeat treatment sometimes needed. The article covers candidacy, Korea travel planning, preparation, recovery, warning signs, follow-up, and alternatives such as antiperspirants, Botox, microwave thermolysis, and gland removal.
Updated: Sep 18, 2026

Hyperhidrosis Surgery in Korea: ETS Methods, Risks, Recovery, and Travel Planning
Endoscopic thoracic sympathectomy (ETS) uses small chest ports under general anesthesia to permanently interrupt the sympathetic chain for severe primary palmar sweating after non-surgical treatments have failed or are not tolerated. International patients should plan 7–10 postoperative days in Korea, attend follow-up before flying, obtain flight clearance if pleural air is a concern, and arrange
Updated: Sep 18, 2026

